PSSD and small fibre neuropathy: what's known
Told a skin biopsy shows small fibre neuropathy? What the condition is, what is known about it in PSSD, and what you can do.

Some people with post-SSRI sexual dysfunction (PSSD) have had a skin biopsy, a test on a tiny piece of skin, and been told they have small fibre neuropathy, which means damage to the body’s thinnest nerves. As of October 2026 we found no proper study of this, so we don’t know if the antidepressant plays a part, or if it explains PSSD.
Michael took paroxetine (Paxil), an SSRI, in the US in 2018. He told his story to the patient group PSSD Network. Within an hour of the first tablet, he says, he lost almost all feeling in his genitals. He stopped a couple of months later, but the numbness stayed. Later came tingling and burning elsewhere in his body.
In 2023 a nerve specialist, doubtful at first, agreed to look. Michael writes:
“Subsequently, a punch biopsy confirmed my diagnosis, revealing nerve density comparable to someone over 80 years old.”
Nerve density is how many tiny nerve fibres were in the skin sample. When he wrote this, he’d been off the tablets for six years.
So what is small fibre neuropathy, and can a biopsy tell you anything about PSSD?
What is small fibre neuropathy?
It’s damage to the thinnest nerves in the skin, the ones that carry pain, heat and cold. It usually starts in the feet, often as burning, says a 2022 review by nerve specialists.
The usual nerve tests mostly check bigger nerves, the review says. So they can come back “normal” while the smallest nerves go unchecked.
It has turned up with genital numbness before. In 2017, doctors in Boston described two young men whose genitals had slowly gone numb. Skin samples from their legs showed small fibre neuropathy. The report doesn’t link it to any medicine.
Rosie, president of the PSSD Network, took escitalopram. Watch this extract for what lasting numbness is like. Four years on, she says, “I literally cannot even feel myself peeing”. She’s also had burning and prickling over her body. She feels it’s linked to PSSD, but isn’t certain.

Has anyone with PSSD been found to have it?
Some people say so, but as of October 2026 we found no proper study that tested it.
The one published paper we found describes three men at a clinic for bladder and genital problems in Michigan, US. They had lasting sexual problems after SSRIs, the hair-loss tablet finasteride or the acne medicine isotretinoin. A scan of tiny nerves at the front of the eye found damage in two. The team thinks the nerves may be one part of the problem.
Dr Kenneth Peters, who led it, describes young patients arriving with almost the same symptoms, including numbness. That doesn’t prove nerve damage.

A UK attempt to test more people ran into problems. In March 2023 the drug-safety website RxISK reported delays at a Sheffield hospital. Separately, it shared one person’s biopsy result: normal for their age. We found no later results.
Can a skin biopsy show whether I have PSSD?
No. It can show small fibre neuropathy, but not what caused it, or why your genitals feel numb.
PSSD is when problems last after stopping an SSRI or SNRI antidepressant, such as sertraline or citalopram. At its core is a lasting change in how the genitals feel, often numbness. The checklist that doctors and researchers drew up in 2022 also lists feeling emotionally numb, problems with concentration and memory, and changes in the skin and other senses.
The biopsy is a small piece of skin, usually taken near the ankle. A lab counts the tiny nerve fibres in it and compares the count with what’s normal for your age and sex.
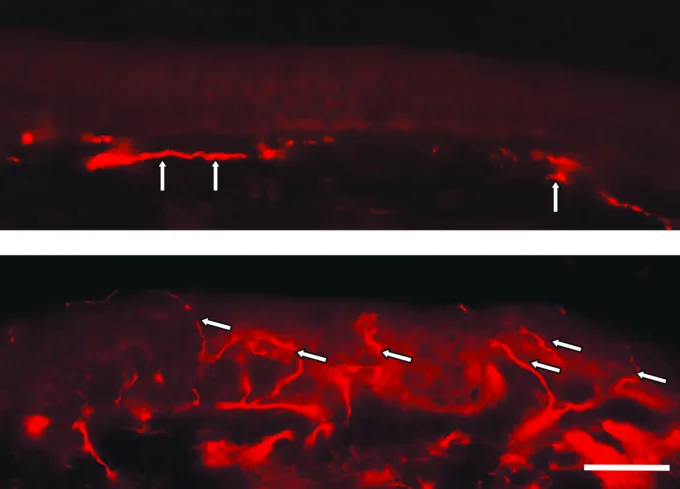

The 2022 review asks how a leg sample could explain pain elsewhere, such as in the pelvis. Its authors also warn that doctors now often give the diagnosis whenever a count is low. One result, they say, means little on its own.
As of January 2025, a patient-run group called INIDA had collected 56 test results from people with PSSD, mostly skin biopsies. It said about 7 in 10 showed small fibre neuropathy. It isn’t a study. People whose test found it may be likelier to send it in, and labs disagree on what counts as low, as the group itself notes.
No reliable figure exists for how many people with PSSD have it.
For how sex feels, the PSSD checklist says “there are no available tests”. You don’t need a test to report PSSD.
What can I do?
These medicines help many people. If you have side effects, that’s a decision for you and your prescriber. Don’t stop suddenly.
If things haven’t lifted since you stopped, give your GP your dates: “Sertraline 50 mg from January 2023, last tablet March 2024.” Describe every change, not only the sexual ones. If your feet burn, tingle or feel numb, say so: the NHS says to see a GP about that.
Our page on genital numbness covers other causes to rule out.
Three questions for your GP
- Could a nerve problem, or something like diabetes, explain any of this?
- If you suggest a test, what would it show, and what wouldn't it?
- Can this go on my record and be reported to the Yellow Card scheme?
You could start with: “Since taking my antidepressant, my genitals feel numb, and it hasn't gone since I stopped.”
Report it: it helps everyone
A doctor’s note helps you. A report to the medicines regulator helps everyone else: it is how patterns get noticed.
- No proof needed. A suspicion is enough, even years after stopping.
- Where: the Yellow Card scheme in the UK, MedWatch in the US.
- Use the right words. If symptoms continued after stopping, write Post-SSRI sexual dysfunction (MedDRA 10086208).
Our reporting guide walks you through it
What else do people ask?
Is PSSD in the brain or in the nerves? Nobody knows yet. The Michigan eye scans found signs of nerve damage. A small London study of nerve tests points to the brain. Our pages on numbness studies and why SSRIs affect sex cover both.
Could my numbness be anxiety or depression? Two researchers who helped write the checklist say no mental health condition numbs the genitals, while SSRIs are known to. Our page on genital numbness after SSRIs explains more.
If it’s nerve damage, is it for good? For some people PSSD has lasted years after stopping. Nobody knows yet who will be affected, or whether it will ease. A biopsy doesn’t answer that either.
Michael’s biopsy came about five years after his first tablet. If your genitals have felt different since your last tablet, write down where and when, and report it. More on our PSSD page.
Sources
- Healy D, Bahrick A, Bak M and colleagues. Diagnostic criteria for enduring sexual dysfunction after treatment with antidepressants, finasteride and isotretinoin. Int J Risk Saf Med 2022;33(1):65-76. Proposed criteria. Necessary criterion: “An enduring change in somatic (tactile) or erogenous (sexual) genital sensation after treatment stops.” Ancillary non-sexual symptoms “may include” “emotional numbing”, “other sensory problems involving skin, smell, taste or vision” and “cognitive impairment”. Section 9: quantitative sensory testing of the penis “may be helpful in assessing somatic sensation”; “Erogenous sensation is poorly understood and there are no available tests.”
- Lundbeck Limited. Cipralex (escitalopram) patient information leaflet, electronic medicines compendium (UK), leaflet revised May 2025. Section 2: sexual problems “have continued after stopping treatment” in some cases.
- PSSD Network. Patient spotlight: Michael, undated, read 28 October 2026. His own account, quoted as published: paroxetine from 2018, genital numbness within an hour of the first pill, stopped “a couple of months later”; later “tingling and burning sensations in my extremities”; in 2023 a neurologist, after brain and spine MRI and EMG, arranged a punch biopsy. “I have now been off the drug for six years.”
- Stachelek J, Zwaans BMM, Shtein R, Peters KM. Insights into the peripheral nature of persistent sexual dysfunction associated with post-finasteride, post-SSRI and post-accutane syndromes: lessons learned from a case study. Int Urol Nephrol 2025;57(8):2387-2394. Corewell Health William Beaumont University Hospital, Michigan. Three men, retrospective chart review. “Peripheral neuropathy was noted in two patients via corneal confocal microscopy, however central symptoms remain.” Read as the abstract only; it names retinoids, finasteride or saw palmetto, and SSRIs as the medicines implicated, without saying which man took which. The paper also reports a treatment; we do not describe it.
- Lauria G, Faber CG, Cornblath DR. Skin biopsy and small fibre neuropathies: facts and thoughts 30 years later. J Neurol Neurosurg Psychiatry 2022;93(9):915-918. Open access. Small fibres are those “subserving nociception and thermal sensation”; SFN affects somatic and “to a lesser extent autonomic” thin fibres; classically length-dependent, “the feet are first affected”, “burning feet”. “The intrinsic limitations of routine nerve conduction studies” have been overcome “by skin biopsy at the ankle”; normal values are “sex and age-adjusted”. “Without context an abnormal laboratory value or imaging study has no intrinsic meaning.” The diagnosis is “frequently applied to any condition in which IENF at any site is found reduced”. “How could one or more skin biopsies at the lower limb address this issue in patients with either non-localised pain or pain localised to another site?”
- AbdelRazek MA, Chwalisz B, Oaklander AL, Venna N. Evidence of small-fiber neuropathy (SFN) in two patients with unexplained genital sensory loss and sensory urinary cystopathy. J Neurol Sci 2017;380:82-84. Massachusetts General Hospital, Boston. Two men aged 21 and 28 with progressive genital numbness; leg skin biopsies diagnostic of small fibre neuropathy; no medicine named as a cause.
- RxISK. PSSD patients needed for small fibre neuropathy investigation, 31 October 2022: planned clinic in Sheffield with skin biopsy, “regarded as the gold standard for detecting small fibre neuropathy”. And PSSD and small fibre neuropathy investigation runs into problems, 8 March 2023: the department was waiting for permission to accept “patients who don’t fit the standard picture”. In a separate update, one biopsy result from a person with PSSD was “within the normal range for the person’s age” (not said to be from Sheffield). Nerve conduction “predominantly assesses large nerve fibres”. We found no later write-up of results (search 28 October 2026).
- INIDA (Iatrogenic Neuroimmune Disease Association), a patient-run group. Clinical findings from PSSD community members, version 2.0, data compilation dated 22 January 2025 (PDF, not linked). Section 5.3: “We have received 56 reports in total of SFN diagnostics (50 skin biopsies and 6 QST’s).” Section 8.2 gives “39 out of 56 patients (70%) being positive for SFN”. It adds: “in theory you could be negative at one lab, while positive at another one.” Section 8 also names “selection bias” in results reported by patients. Read 28 October 2026 in the copy uploaded June 2025 (still the 22 January 2025 compilation). Results shared by patients, not a study; not peer reviewed. We cite it only for this count and do not share its views on causes or treatment.
- Valnarov-Boulter I, Noronha A, Malladi P and colleagues. Genital sensory loss in persistent sexual dysfunction following SSRI exposure. International Continence Society 2026, abstract 302. Pelvic nerve tests (somatosensory evoked potentials) normal in 8 of 9 people with PSSD; “Normal SEP studies effectively exclude a significant peripheral large-fibre neuropathy”; the authors suggest “a centrally-mediated mechanism”. Conference abstract.
- Healy D, Mangin D. Post-SSRI sexual dysfunction: barriers to quantifying incidence and prevalence. Epidemiol Psychiatr Sci 2024;33:e40. “No mental health disorder causes anaesthesia of the genitals, whereas it is a documented effect of serotonin reuptake inhibitors.”
- NHS. Peripheral neuropathy, page last reviewed 10 October 2022. Symptoms include “numbness and tingling in the feet or hands” and “burning, stabbing or shooting pain”; see a GP about early symptoms such as “pain, tingling or loss of sensation in the feet”.
- GOV.UK. Report a problem with a medicine or medical device.
- Moral Medicine, Interview with PSSD Network President Rosie, 9 July 2024, extract 25:48 to 29:12 (the same extract as on our pages on what PSSD feels like and PSSD blood tests). From the YouTube automatic captions. Asked about her symptoms “four years later”, she says “I literally cannot even feel myself peeing” (26:02). Also: “I’ve had like random burning and like prickling Sensations over my body as I like I’m not sure if that’s 100% linked to pssd I feel like it is because it all kind of came on around the same time” (28:15 to 28:25). Her story on our site: Interview with Rosie.
- SIDEfxHUB, Interview with Dr. Kenneth Peters, PFS / PAS / PSSD Summit 2026, April 2026, extract 2:56 to 5:06 (the same extract as on our numbness studies page). Paraphrased, not quoted. Dr Peters is a urologist at Corewell Health William Beaumont University Hospital, Michigan, and senior author of source 4.
- Burlina AP, Sims KB, Politei JM and colleagues. Early diagnosis of peripheral nervous system involvement in Fabry disease and treatment of neuropathic pain: the report of an expert panel. BMC Neurology 2011;11:61. Figure via Wikimedia Commons, CC BY 2.0, converted to WebP and resized.
Sources checked on 28 October 2026. AI-assisted writing and review, not clinical review.
640+ people have joined the registry.
Join them, then report your side effects.
Free. Sign up takes 2 minutes.